Medical Device Penetration Testing for FDA Submissions
Define what needs testing, the evidence you will receive, and the time your engineering team needs for fixes. We scope testing around your threat model, device version, and patient-safety risks, with a fixed fee agreed before work begins.
The short answer
What is medical device penetration testing, and what does the FDA need from it?
Medical device penetration testing examines the attack paths across your device and its connected ecosystem. The agreed scope can include hardware, firmware, wireless, mobile apps, APIs, and cloud services. You receive a Test Plan, Test Cases, and Test Report with threat-model traceability and retest evidence. Choose standalone testing when your other cybersecurity documentation is in place, or the FDA Premarket Cybersecurity Package when you need the broader documentation and testing engagement. Scope, access, deliverables, and dates are agreed before testing.
275+ FDA submissions supported, zero cybersecurity rejections.
We agree the device version, interfaces, test environment, access, and rules of engagement before work begins. Your threat model and cybersecurity hazard analysis determine the attack paths we test, not an asset count alone.
01
Medical device
Firmware · stored keys · debug ports
Secure boot & signed updates
02
Wireless link
Bluetooth · Wi-Fi · pairing
Authentication & replay resistance
03
Companion app
Local data · sessions · commands
Authorization & secure storage
04
Cloud & portal
APIs · accounts · update delivery
Access control & tenant isolation
Illustrative connected system. Scope follows your actual interfaces and architecture; not every device has all four areas.
Interfaces we can test
Hardware and debug ports, firmware and update paths, BLE and Wi-Fi, companion mobile apps, APIs, web portals, and cloud services. Clinical protocols such as DICOM, HL7, and FHIR are included when relevant to your device and agreed scope.
What the quote separates
Penetration testing includes dynamic, adversarial testing and the Test Plan, Test Cases, and Test Report. SAST, software composition analysis, SBOM work, and threat-model rework are scoped separately or bundled explicitly. This is security testing, not general software testing.
Unlimited retests until every finding with uncontrolled risk is closed. Risk disposition remains a documented manufacturer decision.
In their words
Backed by MedTech leaders.
HT
"Blue Goat Cyber's depth of expertise was impressive. We had no in-house cybersecurity experience, and their team guided us through every step of the FDA process. The penetration testing and SBOM testing were thorough and gave us complete confidence."
Hank Tucker
CEO · MedTech Manufacturer
"Blue Goat's niche expertise in FDA-facing cybersecurity made all the difference. Their reports were built with the FDA's expectations in mind; it gave us confidence that we were submitting exactly what reviewers want to see."
Scott Odland
Solutions Architect · Rhaeos
"The timeliness of this project exceeded my expectations - this was not my experience with other vendors. Blue Goat Cyber delivered a thorough, detailed report and complete testing faster than I anticipated, without compromising quality."
Tim Sandberg
VP of IT Operations · Matrix One
Attack surface
Which security checks are in scope?
The FDA's February 3, 2026 guidance describes security requirement verification, threat mitigation verification, vulnerability testing, and penetration testing. We agree the applicable checks for your device and record exclusions. SAST, software composition analysis, and SBOM work are separate unless explicitly bundled.
Security requirements and threat mitigations
Authentication, authorization, and privilege boundaries
Secure boot, signed updates, cryptography, and key handling
Abuse scenarios traced to the threat model
Security findings linked to patient-harm context
Dynamic vulnerability and adversarial testing
Protocol fuzzing and malformed-input testing
Known-vulnerability checks on in-scope components
Manual authorization and business-logic testing
Vulnerability chaining across connected components
Static code analysis and SBOM assessment quoted separately
Attack surface
What we test in a medical-device pen test
The full stack a connected medical device exposes, from the clinician portal down to the implant firmware. Every layer is in scope when it matters to patient safety or regulatory submission.
01Clinician / hospital portal
02Cloud APIs and data plane
03Cellular / Wi-Fi backhaul
04Mobile companion app
05BLE / RF / wireless telemetry
06Service / maintenance interfaces
07Device firmware + OS
08Internal buses (CAN, EtherCAT, I2C, SPI)
09Microcontroller boot chain
Layers shown outermost (top) to innermost (bottom). Dashed rows are part of the surrounding system but out of scope for this view.
How it works
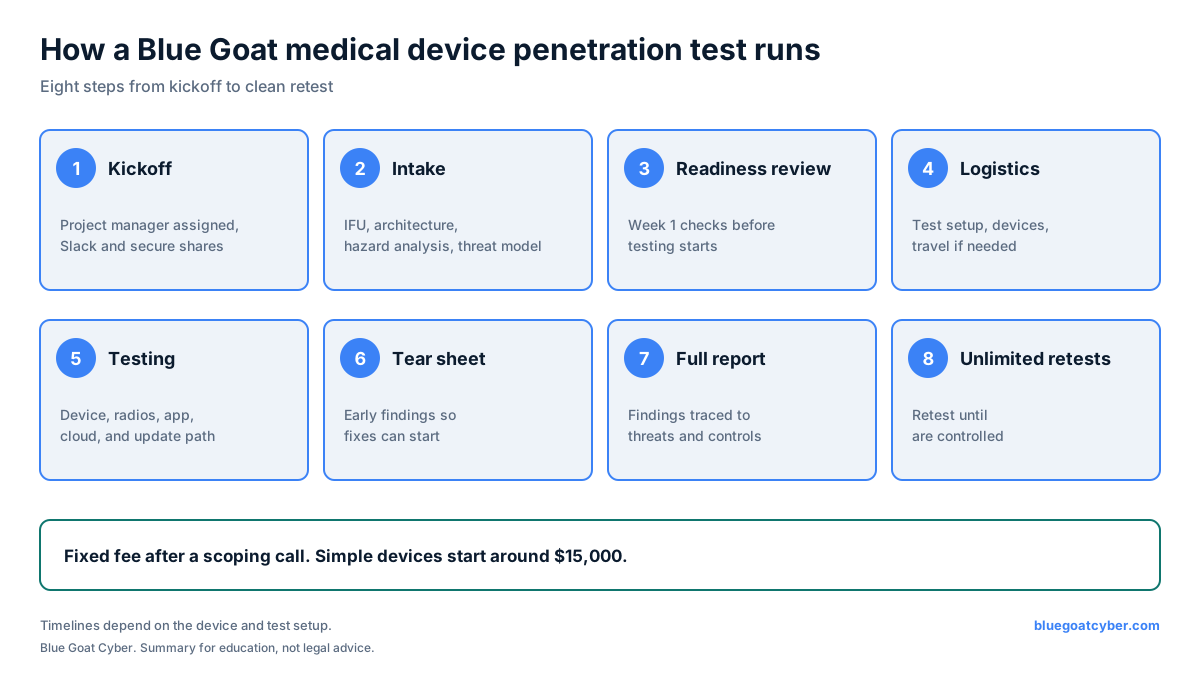
What happens from kickoff through retesting?
Your project manager coordinates access, testing, reporting, and engineering handoffs. The schedule separates our testing work from your remediation work.
01
Contract and kickoff
We assign your project manager and confirm the scope, dates, device build, contacts, and rules of engagement.
02
Shared workspace
We set up a private Slack channel and secure document shares.
03
Intake and readiness
We review the IFU, architecture, threat model, and cybersecurity hazard analysis. A light review is part of scoping; missing documentation or deeper rework is quoted separately.
04
Test logistics
We confirm device shipping or on-site arrangements, representative non-clinical units, test accounts, and environment access.
05
Testing
We run the agreed Test Plan against the identified device version and connected components.
06
Findings summary
You receive a tear sheet so engineering can begin remediation before the full report is complete.
07
Full evidence set
We deliver the Test Plan, Test Cases, and Test Report with findings, reproduction evidence, and threat-model traceability.
08
Fixes and retests
Your engineers implement fixes. We retest and update the evidence, with unlimited retests until every finding with uncontrolled risk is closed. Risk disposition remains your documented decision.
Pricing guidance
How is the fixed fee determined?
A simple device starts at about $15,000, with a reasonable turnaround and no travel. You receive a fixed-fee quote within 24 hours of the scoping call. The quote identifies device versions, interfaces, deliverables, assumptions, and retest coverage.
Targeted testing
Fixed fee after scoping
A defined surface or evidence gap. The report states exclusions; a targeted test does not represent coverage of an entire connected device.
Agreed interface and attack paths
Test Plan, Test Cases, and Test Report
Findings and retest evidence
Connected-device testing
Fixed fee after scoping
Testing across the device and the connected components identified by your threat model.
Hardware, firmware, and wireless as scoped
Mobile, API, and cloud as scoped
Traceability and patient-harm context
Broader premarket engagement
Fixed fee after scoping
The FDA Premarket Cybersecurity Package adds the agreed documentation and security activities beyond penetration testing.
Threat modeling and cybersecurity risk assessment
Security architecture and SBOM work
Security testing, labeling, and vulnerability management planning
What drives the price
Interfaces, components, and device versions
Source code, architecture, and threat-model availability
Hardware samples and test-environment readiness
Cloud configuration and tenant boundaries
Travel, testing restrictions, and submission schedule
SAST, software composition analysis, SBOM work, and threat-model rework are separate unless explicitly bundled. Changes to the agreed device versions or interfaces require a scope review.
Standards medical device penetration testing maps to
Every medical device penetration testing engagement produces evidence aligned to the regulatory and consensus standards FDA reviewers and notified bodies expect to see, traceable, complete, and ready to drop into your ISO 13485 quality system.
Featured site-wide
FDA 2026 Guidance Featured
FDA Premarket Cybersecurity Guidance (Feb 3, 2026)
Recommends risk-based cybersecurity evidence, including threat modeling, architecture views, and testing. An SPDF is encouraged, not mandatory; Section 524B separately establishes statutory duties for covered cyber devices.
ANSI/AAMI SW96 Featured
Medical Device Security Risk Management
The consensus standard for medical device security risk management, asset, threat, vulnerability, likelihood, severity, and residual risk acceptability.
ISO 14971 Featured
Medical Device Risk Management
Foundational risk management standard. Cybersecurity risk is tied directly to patient-safety risk in the 14971 file.
IEC 62443-4-1
Secure Product Development Lifecycle
Industrial-strength secure-development-lifecycle requirements applied to connected medical devices.
NIST SP 800-115
Technical Guide to Information Security Testing
Reference methodology for planning, executing, and reporting security testing.
Notable incidents
Public premarket cybersecurity history
Recalls, CISA ICS-MA advisories, and disclosed research that shape what reviewers ask about, and what this engagement is built to cover.
Fixed fee after a scoping call. Simple devices start around $15,000, with unlimited retests until every finding with uncontrolled risk is closed. View the full graphic and text version
DICOM testing pre-check
Imaging device, PACS, or viewer? Answer these and get a one-page scoping sheet for your DICOM security test. Takes about two minutes.
Which DICOM services does it expose?
Pick everything the device answers on its DICOM port.
Which transfer syntaxes does it support?
What role does it play on the imaging network?
What sits in front of the DICOM port?
What test environment can you give us?
Please don't enter confidential details here.
We'll email you a link to book a free discovery call; the fixed-fee proposal follows the call. Want to try the protocol yourself first? Download the DICOM seed corpus and read the DICOM fuzzing guide.
Questions before booking a medical device pen test
Ready to start Medical Device Penetration Testing?
Medical Device Penetration Testing - scoped, fixed-fee, built for FDA premarket submissions.
Define what needs testing, the evidence you will receive, and the time your engineering team needs for fixes. We scope testing around your threat model, device version, and patient-safety risks, with a fixed fee agreed before work begins.
You receive the Test Plan, Test Cases, and Test Report. Together they connect scope, execution, findings, and retests. A letter of attestation is not needed for FDA penetration testing.
Before testing
Penetration Test Plan
The agreed device build, environment, attack paths, methods, tools, schedule, rules of engagement, and tester independence. Scope is anchored to your threat model.
During execution
Penetration Test Cases
Test identifiers link threat scenarios and security requirements to methods, expected and actual results, and findings. Coverage and limitations remain visible.
Results and retests
Penetration Test Report
Tester independence and expertise, scope, duration, methods, findings, reproduction evidence, remediation guidance, patient-harm context, and retest status. Unresolved findings and manufacturer risk disposition remain documented.
Your engineers implement fixes. We provide unlimited retests until every finding with uncontrolled risk is closed, within the agreed device versions and interfaces. Risk disposition and any residual-risk acceptance remain your documented decisions.
Do you need standalone testing or the full package?
Choose based on the evidence you already have and the work still needed. Penetration testing is a defined security activity, not a complete premarket cybersecurity submission by itself.
Standalone penetration testing
For teams with a threat model, cybersecurity hazard analysis, and the other documentation in place, or teams closing a specific testing gap.
Dynamic and adversarial security checks across the agreed surfaces.
Test Plan, Test Cases, Test Report, and retest evidence.
SAST, software composition analysis, SBOM work, and threat-model rework are separate unless explicitly bundled.
FDA Premarket Cybersecurity Package
For teams that need the broader cybersecurity documentation and testing engagement coordinated together.
Threat modeling, cybersecurity risk assessment, and security architecture.
SBOM work, security testing, labeling, and vulnerability management planning.
The applicable work is defined for your device and submission pathway, with a fixed fee after scoping.
This is cybersecurity testing, not general software testing or software validation. Testing evidence does not establish regulatory acceptance.
What determines your testing timeline?
We agree dates after reviewing the device, scope, and available inputs. A testing schedule must leave room for your engineers to fix findings and for us to retest. There is no universal completion window for every device.
Before testing
Have the IFU, software architecture, threat model, and cybersecurity hazard analysis available. Confirm device samples, build versions, test accounts, environment access, shipping, and any on-site restrictions.
During testing
The number of interfaces, connected components, access depth, and testing restrictions affect duration. A tear sheet gives engineering a findings summary before the full report is complete.
After testing
Your team implements fixes. Fix availability and retest results affect the final evidence date. New builds or changed interfaces may require a scope review.
At the scoping call
Bring your submission date and identify any missing inputs. You receive a fixed-fee quote within 24 hours. That quote turnaround is separate from the testing and remediation schedule.
A CVSS score says how easy an attack is. It doesn't say whether a patient could be hurt. We link every finding to your threat model and hazard analysis, so its risk is rated in terms of patient harm and FDA reviewers can follow the chain from threat to fix.
A
Threat model
Names the threats and attack paths. Each test case traces back to a threat.
Threat: an attacker nearby sends commands over Bluetooth without pairing.
B
Hazard analysis
Names what could hurt a patient if the device misbehaves (ISO 14971).
Hazard: the device delivers the wrong therapy setting.
1
Pen test finding
What we proved during testing, tied to the threat it came from.
Finding: therapy settings can be changed over Bluetooth without authentication.
2
Exploitability
How easy the attack is, scored with CVSS.
Low skill needed, attacker must be within Bluetooth range.
3
Patient-harm risk
Exploitability combined with the linked hazard's severity. This rating, not CVSS alone, sets priority.
Rated high: a wrong therapy setting can harm the patient.
4
Fix and retest
The fix is verified in a retest, and the full chain goes into your FDA report.
Pairing and command authentication added, retest passes.
The example lines show an illustrative case, not a specific client engagement.
For medical devices, both Blue Goat and the FDA recommend white-box testing. Reviewers expect testers to leverage source, firmware, and threat models, black-box alone routinely leads to deficiencies.
Capability
Black-box
Gray-box
White-box
Source code access
Firmware / binaries
Threat model & architecture
Authenticated test paths
Deep logic + business-flow flaws
Aligned with FDA expectations
Scope coverage per test-day
Yes Partial No
References
Why the FDA and AAMI point to white-box
Premarket guidance and consensus standards both expect testers to leverage source code, design artifacts, and threat models, not just an external view of the device.
Calls for security testing that demonstrates device resilience using design documentation, threat models, and source-level analysis, not black-box probing alone.
Requires sponsors to provide reasonable assurance that the device and related systems are cybersecure, which reviewers read as evidence-backed, white-box-informed testing.