Medical Device Penetration TestingWhite-Box Testing & FDA-Ready Reports.
Struggling to meet the FDA's cybersecurity testing requirements? We identify vulnerabilities and deliver FDA-ready reports - fast, accurate, and aligned with current guidance. We recommend white-box testing for medical devices, and so does the FDA.
The short answer
What is medical device penetration testing, and what does the FDA need from it?
Medical device penetration testing is white-box security testing of a device and everything it connects to - firmware, hardware debug interfaces, wireless radios, the companion app, the APIs, and the cloud back end - run against your source code, architecture, and threat model. For an FDA submission it has to do four things the 2026 premarket guidance calls out: verify security requirements, verify threat mitigations, run vulnerability testing, and run true penetration testing. The deliverable is an FDA-formatted report with CVSS and ISO 14971 patient-harm ratings, threat-model traceability, and documented tester independence, scope, methods, and results.
We agree the device version, interfaces, test environment, access, and rules of engagement before work begins. Your threat model and cybersecurity hazard analysis determine the attack paths we test, not an asset count alone.
01
Medical device
Firmware · stored keys · debug ports
Secure boot & signed updates
02
Wireless link
Bluetooth · Wi-Fi · pairing
Authentication & replay resistance
03
Companion app
Local data · sessions · commands
Authorization & secure storage
04
Cloud & portal
APIs · accounts · update delivery
Access control & tenant isolation
Illustrative connected system. Scope follows your actual interfaces and architecture; not every device has all four areas.
Interfaces we can test
Hardware and debug ports, firmware and update paths, BLE and Wi-Fi, companion mobile apps, APIs, web portals, and cloud services. Clinical protocols such as DICOM, HL7, and FHIR are included when relevant to your device and agreed scope.
What the quote separates
Penetration testing includes dynamic, adversarial testing and the Test Plan, Test Cases, and Test Report. SAST, software composition analysis, SBOM work, and threat-model rework are scoped separately or bundled explicitly. This is security testing, not general software testing.
Unlimited retests until every finding with uncontrolled risk is closed. Risk disposition remains a documented manufacturer decision.
Why Most Pen Testing Fails Medical Devices
Generic penetration testing firms lack the understanding of unique device architecture, patient risks, and regulatory demands. Their reports may be thorough, but not FDA-compliant - and they almost always default to black-box only.
Black-box-only testing
The FDA expects testers to leverage source code, threat models, and architecture (white-box). Black-box-only engagements miss the deep flaws reviewers ask about - and lead to deficiencies.
Incomplete Testing
Generic vendors miss firmware, wireless, and embedded paths unique to medical devices.
Wrong Reporting Format
Reports without FDA-aligned structure, traceability, and evidence get rejected by reviewers.
In their words
Backed by MedTech leaders.
HT
"Blue Goat Cyber's depth of expertise was impressive. We had no in-house cybersecurity experience, and their team guided us through every step of the FDA process. The penetration testing and SBOM testing were thorough and gave us complete confidence."
Hank Tucker
CEO · MedTech Manufacturer
"Blue Goat's niche expertise in FDA-facing cybersecurity made all the difference. Their reports were built with the FDA's expectations in mind; it gave us confidence that we were submitting exactly what reviewers want to see."
Scott Odland
Solutions Architect · Rhaeos
"The timeliness of this project exceeded my expectations - this was not my experience with other vendors. Blue Goat Cyber delivered a thorough, detailed report and complete testing faster than I anticipated, without compromising quality."
Tim Sandberg
VP of IT Operations · Matrix One
Attack surface
The four types of testing the FDA expects - and the full attack surface
The FDA's February 3, 2026 premarket cybersecurity guidance describes security requirement verification, threat mitigation verification, vulnerability testing, and penetration testing. We define the applicable security checks and interfaces in your scope; SAST, software composition analysis, and SBOM work are separate unless explicitly bundled.
1. Security requirement verification
Authentication and session management against the stated design
Authorization, role separation, and privilege boundaries
Cryptography in transit and at rest, plus key storage and rotation
Secure boot, code signing, and firmware update integrity
Audit logging, event forensics, and tamper evidence
Every requirement traced back to the threat model and design inputs
2. Threat mitigation verification
Each STRIDE threat from your model exercised against its stated control
Abuse cases and misuse cases run to failure, not just happy-path checks
Residual risk documented where a mitigation is only partial
Patient-harm impact rated under ISO 14971, not just CVSS
Multi-patient harm and network-of-devices scenarios
Traceability matrix reviewers can audit line by line
3. Vulnerability testing, SAST and DAST
Static application security testing (SAST) and secure code review across firmware and application source
Dynamic application security testing (DAST) against running services and web interfaces
Software composition analysis and SBOM-driven CVE triage with VEX statements
Protocol and input fuzzing across BLE, serial, USB, REST, MQTT, and gRPC
Known-vulnerability checks against chipsets, RTOS, kernels, and third-party libraries
Malformed input, robustness, and error-handling testing
4. Penetration testing across the real attack surface
Hardware teardown, JTAG/UART/SPI access, firmware extraction and reverse engineering
Wireless: BLE pairing and GATT abuse, Wi-Fi (WPA2/WPA3), cellular/NB-IoT, and NFC
Mobile companion apps on iOS and Android, including OWASP MASVS coverage
Web apps and APIs against OWASP ASVS and the OWASP API Top 10
Cloud back end, IAM, tenant isolation, containers, and Kubernetes workloads
Interoperability surfaces: DICOM, HL7/FHIR, and hospital network integration
Attack surface
What we test in a medical-device pen test
The full stack a connected medical device exposes - from the clinician portal down to the implant firmware. Every layer is in scope when it matters to patient safety or regulatory submission.
01Clinician / hospital portal
02Cloud APIs and data plane
03Cellular / Wi-Fi backhaul
04Mobile companion app
05BLE / RF / wireless telemetry
06Service / maintenance interfaces
07Device firmware + OS
08Internal buses (CAN, EtherCAT, I2C, SPI)
09Microcontroller boot chain
Layers shown outermost (top) to innermost (bottom). Dashed rows are part of the surrounding system but out of scope for this view.
How it works
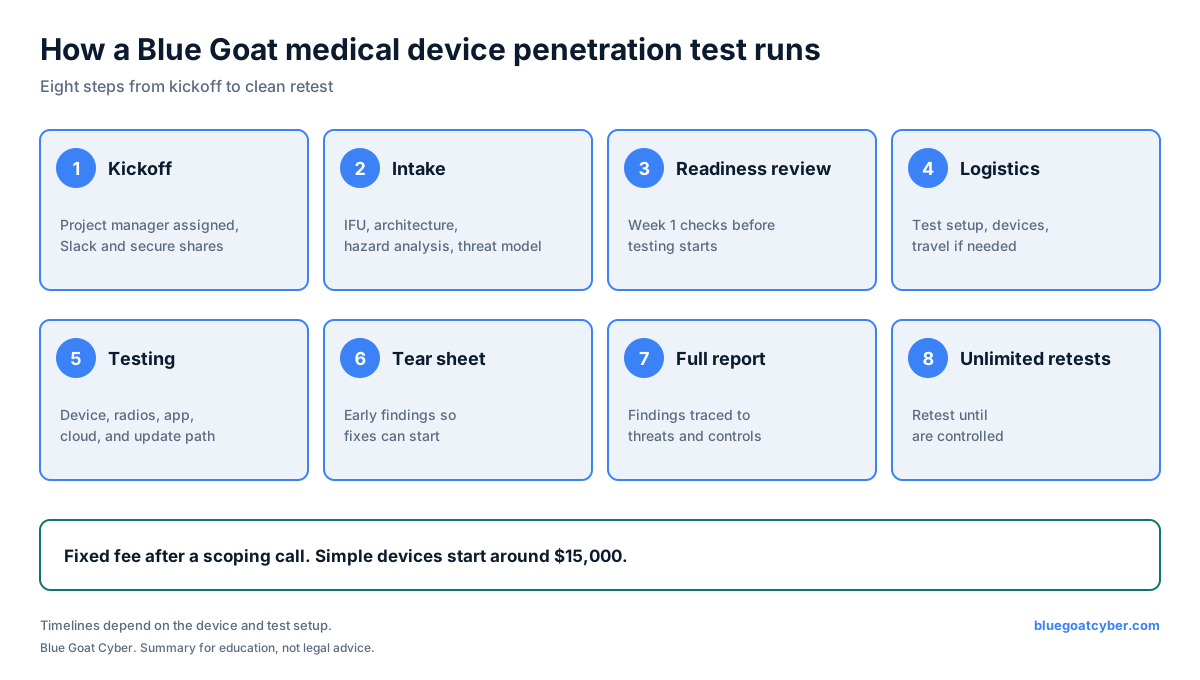
How an FDA pen test engagement runs
Every project gets a dedicated project manager from kickoff to final report, so you always know what is happening and what we need from you.
01
Kickoff
Once the contract is signed, we assign your project manager and hold a kickoff call to confirm scope, dates, and contacts.
02
Shared workspace
We set up a private Slack channel for day-to-day questions and secure shares for exchanging documents.
03
Intake
We collect the Instructions for Use (IFU), Software Architecture Document (SAD), hazard analysis and threat model. Testing starts only once a threat model and hazard analysis exist. No threat model or hazard analysis yet? We can build them. Already have them? We can run a gap assessment of both.
04
Logistics
We confirm whether devices ship to our lab or we travel to you, and that units, accounts, tools and the test setup are ready.
05
First round of testing
We run the test plan against the exact device version you plan to submit.
06
Tear sheet
You get a short findings summary right after testing, so engineering can start fixing before the full report is done.
07
Full report
Test Plan, Test Cases and Test Report, with every finding traced to a threat and a patient harm.
08
Remediation and retesting
Your engineering team makes the fixes. We verify them and update the evidence, with unlimited retests until every finding with uncontrolled risk is closed. Risk disposition remains your documented decision.
What's included
Reviewer-ready deliverables in one engagement
Every medical device penetration testing engagement ships with the artifacts FDA reviewers expect to see - traceable, complete, and aligned with current guidance.
Device, firmware, and embedded testing - hardware teardown, JTAG/UART/SPI bus access, firmware extraction and reverse engineering, and exploitation of the secure boot, debug, and update paths. Done by operators who have tested infusion pumps, monitors, surgical robots, and implantables.
Companion app and cloud API coverage - iOS/Android binary analysis, BLE pairing/GATT attacks, REST/MQTT/gRPC fuzzing, authentication and authorization testing, and tenant-isolation checks. We test the device as patients and clinicians actually use it, not in isolation.
FDA-ready penetration test reports - executive summary, methodology, CVSS-scored findings tied to your threat model, reproduction steps, and documented tester independence, scope, methods, and results. Reviewer-ready, not a generic IT security PDF.
Remediation guidance and re-test included - written fix recommendations per finding, engineer-to-engineer support during remediation, and unlimited retests until every finding with uncontrolled risk is closed, inside the fixed fee. Accepted residual risks remain documented in your risk file.
Pricing guidance
Fixed-fee penetration testing pricing
A simple device starts at about $15,000, with a reasonable turnaround and no travel. After the scoping call, you receive a fixed-fee quote in writing within 24 hours. The agreed scope includes the Test Plan, Test Cases, Test Report, and unlimited retests until every finding with uncontrolled risk is closed.
Scoped / single surface
Fixed fee after scoping
A targeted scope for a simple device or a specific attack surface, such as firmware, BLE, or a cloud API. Suitable for vulnerability investigation or closing a defined evidence gap; it is not a substitute for full-system submission coverage.
One interface tested to full depth
Dynamic and adversarial checks suited to the surface
CVSS and ISO 14971 rated findings
Retests until uncontrolled risks are closed
Test Report with scope stated
Connected device (most common)
Fixed fee after scoping
Typical Class II connected device: firmware, hardware interfaces, BLE or Wi-Fi, companion app, REST APIs, and cloud back end. Full-attack-surface coverage for a 510(k) or De Novo.
Security checks mapped to the agreed threat model
Firmware, wireless, mobile, API, and cloud
Known-vulnerability checks on in-scope components
Threat-model traceability matrix
Retests until uncontrolled risks are closed
eSTAR-ready Test Report
Platform / PMA ecosystem
Fixed fee after scoping
Class III and PMA submissions, implantables, surgical platforms, multi-device ecosystems, AI/ML inference services, or several products tested in parallel.
Everything in connected device
Multi-device and hospital-network scenarios
Kubernetes and multi-tenant cloud depth
DICOM and HL7/FHIR interoperability testing
AI/ML model and inference-service abuse cases
Coordinated multi-report submission package
What drives the price
Number of distinct interfaces in scope (each radio, app, and API counts)
Whether source code, architecture docs, and a threat model are available for white-box depth
Hardware sample availability and how many units we can destructively test
Cloud complexity: single tenant versus multi-tenant, container and Kubernetes footprint
Regulatory pathway - PMA and De Novo submissions carry deeper evidence expectations than 510(k)
Larger scopes are priced after the scoping call. Timeline is 3 to 5 weeks for most engagements and 6 to 8 weeks for large ecosystems.
Standards medical device penetration testing maps to
Every medical device penetration testing engagement produces evidence aligned to the regulatory and consensus standards FDA reviewers and notified bodies expect to see - traceable, complete, and ready to drop into your ISO 13485 quality system.
Featured site-wide
FDA 2026 Guidance Featured
FDA Premarket Cybersecurity Guidance (Feb 3, 2026)
Recommends risk-based cybersecurity evidence, including threat modeling, architecture views, and testing. An SPDF is encouraged, not mandatory; Section 524B separately establishes statutory duties for covered cyber devices.
ANSI/AAMI SW96 Featured
Medical Device Security Risk Management
The consensus standard for medical device security risk management - asset, threat, vulnerability, likelihood, severity, and residual risk acceptability.
ISO 14971 Featured
Medical Device Risk Management
Foundational risk management standard. Cybersecurity risk is tied directly to patient-safety risk in the 14971 file.
IEC 62443-4-1
Secure Product Development Lifecycle
Industrial-strength secure-development-lifecycle requirements applied to connected medical devices.
NIST SP 800-115
Technical Guide to Information Security Testing
Reference methodology for planning, executing, and reporting security testing.
Notable incidents
Public premarket cybersecurity history
Recalls, CISA ICS-MA advisories, and disclosed research that shape what reviewers ask about - and what this engagement is built to cover.
Imaging device, PACS, or viewer? Answer these and get a one-page scoping sheet for your DICOM security test. Takes about two minutes.
Which DICOM services does it expose?
Pick everything the device answers on its DICOM port.
Which transfer syntaxes does it support?
What role does it play on the imaging network?
What sits in front of the DICOM port?
What test environment can you give us?
Please don't enter confidential details here.
We'll email you a link to book a free discovery call; the fixed-fee proposal follows the call. Want to try the protocol yourself first? Download the DICOM seed corpus and read the DICOM fuzzing guide.
Ready to start Medical Device Penetration Testing?
Medical Device Penetration Testing - scoped, fixed-fee, FDA-ready.
Struggling to meet the FDA's cybersecurity testing requirements? We identify vulnerabilities and deliver FDA-ready reports - fast, accurate, and aligned with current guidance. We recommend white-box testing for medical devices, and so does the FDA.
Fixed fee after a scoping call. Simple devices start around $15,000, with unlimited retests until every finding with uncontrolled risk is closed. View the full graphic and text version
Test depth
White-box vs gray-box vs black-box
For medical devices, both Blue Goat and the FDA recommend white-box testing. Reviewers expect testers to leverage source, firmware, and threat models - black-box alone routinely leads to deficiencies.
Capability
Black-box
Gray-box
White-box
Source code access
Firmware / binaries
Threat model & architecture
Authenticated test paths
Deep logic + business-flow flaws
Aligned with FDA expectations
Scope coverage per test-day
Yes Partial No
References
Why the FDA and AAMI point to white-box
Premarket guidance and consensus standards both expect testers to leverage source code, design artifacts, and threat models, not just an external view of the device.
Calls for security testing that demonstrates device resilience using design documentation, threat models, and source-level analysis, not black-box probing alone.
Requires sponsors to provide reasonable assurance that the device and related systems are cybersecure - which reviewers read as evidence-backed, white-box-informed testing.
Postmarket monitoring and vulnerability handling assume testers have access to internals - the same access white-box pen testing uses premarket.
How an engagement runs
From kickoff to a clean retest in 7 steps
Every project gets a named project manager. The intake documents in step 2 let us trace each finding to your threat model and rate its risk in terms of patient harm, which is what FDA reviewers look for.
1
Kickoff
Contract signed, project manager assigned, shared Slack channel and secure file shares set up.
2
Intake documents
You send the documents below so every finding traces to a threat and a hazard.
3
Logistics
Test setup, device shipping or on-site travel agreed.
4
Testing
Mostly manual, white-box testing of device, firmware, radios, app and cloud.
5
Tear sheet
Early summary of findings so your engineers can start fixing right away.
6
Full report
Test Plan, Test Cases, and FDA-formatted Test Report with CVSS and patient-harm ratings.
7
Retest
We retest your fixes until the findings are closed.
Step 2: what we ask for before testing
Instructions for Use (IFU)
How the device is used and by whom
System architecture
What connects to what
Threat model
What we test against. We can build it if you don't have one.
A CVSS score says how easy an attack is. It doesn't say whether a patient could be hurt. We link every finding to your threat model and hazard analysis, so its risk is rated in terms of patient harm and FDA reviewers can follow the chain from threat to fix.
A
Threat model
Names the threats and attack paths. Each test case traces back to a threat.
Threat: an attacker nearby sends commands over Bluetooth without pairing.
B
Hazard analysis
Names what could hurt a patient if the device misbehaves (ISO 14971).
Hazard: the device delivers the wrong therapy setting.
1
Pen test finding
What we proved during testing, tied to the threat it came from.
Finding: therapy settings can be changed over Bluetooth without authentication.
2
Exploitability
How easy the attack is, scored with CVSS.
Low skill needed, attacker must be within Bluetooth range.
3
Patient-harm risk
Exploitability combined with the linked hazard's severity. This rating, not CVSS alone, sets priority.
Rated high: a wrong therapy setting can harm the patient.
4
Fix and retest
The fix is verified in a retest, and the full chain goes into your FDA report.
Pairing and command authentication added, retest passes.
The example lines show an illustrative case, not a specific client engagement.
Our recommended approach
Why we lead with white-box for FDA submissions
White-box is our default for premarket cyber devices - it's the only depth that gives FDA reviewers full coverage evidence. Gray-box adds credentialed ecosystem testing where it matters. Black-box is reserved for specific post-market or adversary-simulation scenarios.
FDA penetration testing does not need a letter of attestation. We deliver three traceable documents: the Test Plan, Test Cases, and Test Report. The evidence documents tester independence and expertise, scope, duration, methods, findings, and retest results.
Before testing
Penetration Test Plan
Scope anchored to the threat model, the device build and environment, methods, tools, schedule, rules of engagement, and tester independence. Agreed before testing begins.
Traceable execution
Penetration Test Cases
Each case links a threat scenario and security requirement to the test method, expected and actual results, and any finding. Stable identifiers connect the plan to the evidence.
Submission evidence
Penetration Test Report
Tester independence and expertise, scope, duration, methods, findings, patient-harm context, and retest status. Unresolved findings and the manufacturer's documented risk disposition remain visible.
How we stack up
Blue Goat Cyber vs. typical pen test vendors
A transparent, side-by-side look at what you actually get - no vague promises.
Capability
Blue Goat Cyber
Typical Vendor
Technical Capabilities
12+ Years Exclusively Testing Medical Devices
Included
Not offered
Medical Protocol Testing (DICOM, HL7/FHIR, BLE Medical)
Anonymized engagements, from kickoff to FDA clearance
Class II · 510(k)
Wearable Cardiac Monitor
The Problem
Pre-submission penetration test required, with a tight 6-week window before FDA filing. Prior vendor returned a generic scan report that wouldn't satisfy 2026 guidance.
Our Testing
Firmware extraction and binary analysis
BLE pairing and protocol fuzzing
Mobile companion app reverse engineering
Cloud telemetry API authentication review
FDA Outcome
11 findings surfaced, 2 critical pre-filing
FDA-ready report delivered in 4 weeks
510(k) cleared on first review, no cyber deficiencies
Class III · PMA
Implantable Neurostimulator Platform
The Problem
Complex multi-component system (implant, programmer, clinician portal) with PMA filing under FDA 2026 guidance. Needed full SBOM, threat model, and pen test evidence.
Our Testing
Hardware-level analysis of implant and programmer
Proprietary RF protocol security review
Full threat modeling against eSTAR template
Cloud and clinician portal application testing
FDA Outcome
23 findings across 4 components, all remediated pre-filing
SBOM and cybersecurity documentation accepted as filed
PMA reviewed without a single cybersecurity deficiency letter
Real findings
Vulnerabilities we've caught - before the FDA did
A sample of the kinds of issues we surface during medical device penetration tests. Devices and identifiers are redacted.
CriticalWearable cardiac monitor
Hardcoded credentials in BLE pairing
Allowed any nearby attacker to pair and exfiltrate ECG telemetry without user consent.
CriticalClass II infusion pump
Unauthenticated firmware update endpoint
Remote attacker on hospital network could push unsigned firmware, altering dosing logic.
HighContinuous glucose monitor
Plaintext PHI in mobile companion app cache
Patient identifiers and readings recoverable from a lost or stolen phone with no jailbreak.
HighRemote patient monitoring platform
Predictable session tokens on cloud API
Session prediction allowed cross-tenant access to clinician dashboards.
MediumSurgical robotics controller
Debug interface enabled in production firmware
JTAG/UART left open allowed local code extraction and reverse engineering.
MediumConnected diagnostic imaging device
Outdated TLS configuration on telemetry channel
TLS 1.0 fallback exposed device-to-cloud channel to downgrade attacks.
Over 200 FDA and global premarket clearances - from startups to global leaders
Robotic Surgical SystemsIoT-Enabled DiagnosticsImplantable DevicesWearable Health TechComplex IVD SystemsAI-Enabled SaMD
Cost of an FDA cyber deficiency
What does a rejection actually cost?
Plug in your monthly burn, expected launch revenue, and delay window. Most manufacturers see $1M+ exposure on a single cyber hold. Most engagements are a small fraction of that.
Answer a few quick questions about your device classification, connectivity, and FDA path. We'll suggest the right testing track and surface the fastest wins for your submission.
Class I, Class II (510(k)/De Novo), or Class III (PMA)
The certifications that actually break into devices
Our team holds the offensive security certifications real attackers respect, backed by hands-on U.S. government red team and military cyber operations experience.
CISSP
Certified Information Systems Security Professional
CSSLP
Certified Secure Software Lifecycle Professional
OSWE
Offensive Security Web Expert
CRTE
Certified Red Team Expert
CRTL
Certified Red Team Lead
CARTP
Certified Azure Red Team Professional
CBBH
Certified Bug Bounty Hunter
U.S. Government Red Team Experience Military Cyber Operations Manual Business Logic Testing
Industry recognition
Award-winning. Globally recognized.
Our work has been honored by the leading voices in medical device cybersecurity.
2026
Medical Device Cybersecurity Solution of the Year
Medical Tech Outlook
Cover story profiling Blue Goat Cyber as a top industry leader
2025
MedTech Service Provider Excellence Award of the Year
MedTech World Malta 2025
Sponsored by the Malta Medicines Authority
2026
Medical Device Cybersecurity Partner of the Year
MedTech World North America
Inaugural North America Awards, in collaboration with CS Lifesciences